


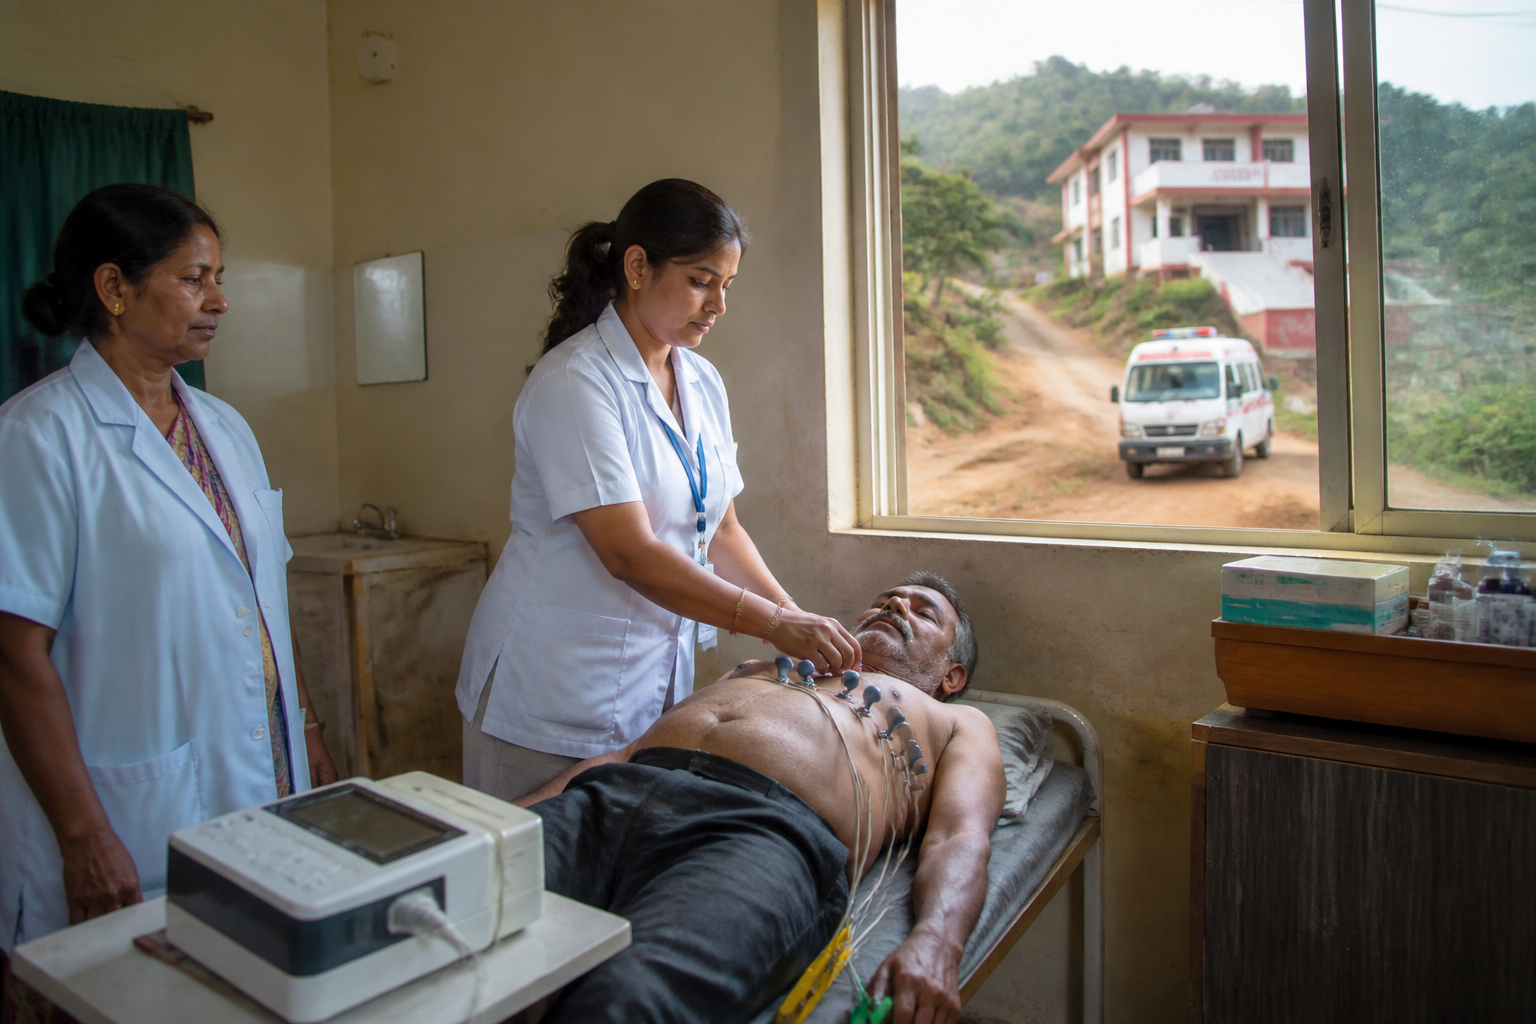
Maharashtra’s STEMI project has conducted nearly 57.91 lakh free electrocardiograms and identified 34,032 critical heart-attack cases, according to state health department data reported by Mid-Day. The figures point to a significant shift in how emergency cardiac care can be organised across a geographically large state: diagnosis begins closer to the patient, specialist interpretation is delivered remotely, and treatment or referral is coordinated through a linked hospital network.
The project is built around a hub-and-spoke model. Government hospitals, rural hospitals and Primary Health Centres function as spokes, where patients with symptoms of a heart attack can receive a free software-enabled ECG. The test is uploaded to the cloud for expert interpretation, which the programme says can be completed in under four minutes. If the ECG confirms a critical ST-Elevation Myocardial Infarction, or STEMI, doctors at the local facility can begin thrombolysis under expert guidance before the patient is transferred to a specialised centre.
That arrangement addresses a basic problem in emergency medicine: the distance between where a patient first seeks help and where advanced treatment is available. A heart attack may begin in a village, small town or district hospital, while angiography and angioplasty are available only at a facility with a cardiac catheterisation laboratory. The project’s significance lies not simply in the number of ECGs performed, but in the attempt to connect these separate levels of the health system into a treatment pathway.
The state’s data shows that the programme has expanded sharply since its initial phase. It began in 12 districts with 39 hub hospitals and 145 spoke facilities. In March 2024, it was expanded to another 22 districts, excluding Mumbai city and its suburban districts. A further 179 health centres were integrated in 2025. The network now includes 2,415 spoke facilities and 96 hub hospitals, according to the figures provided by the health department.
The increase in ECG activity has accompanied that expansion. In 2020-21, the programme conducted 3,369 ECGs and identified 30 critical STEMI cases. ECGs increased to 104,479 in 2021-22, when 1,003 critical cases were identified. The number rose to 233,509 ECGs in 2022-23, with 2,782 critical cases, and to 439,670 ECGs in 2023-24, with 2,642 critical cases.
The programme recorded 1,073,174 ECGs in 2024-25 and identified 6,077 critical STEMI cases. In 2025-26, the number of ECGs rose to 2,339,578, while 13,097 critical cases were detected. During the current financial year, 1,538,558 ECGs had been conducted up to September 27, 2026, and 8,401 critical cases had been identified. The cumulative total reported by the health department is 5,790,963 ECGs and 34,032 critical STEMI cases.
These figures should be read as measures of programme activity and case identification, not as a complete measure of heart-attack incidence across Maharashtra. The data shows how many tests were conducted through the project and how many critical cases were detected within its network. It does not, in the supplied material, establish how many patients ultimately received angioplasty, their survival outcomes, the time taken from symptom onset to treatment, or how the project compares with cardiac emergency care outside the network.
That distinction is important for evaluating a public health infrastructure programme. A rising number of ECGs can reflect wider coverage, increased awareness, improved access to testing or a larger number of facilities reporting into the system. The rise in detected STEMI cases may similarly reflect better identification of cases that might previously have gone undiagnosed at smaller facilities. The available data confirms that the network is being used at a much larger scale, but it does not by itself establish the programme’s clinical outcomes.
The institutional design is as important as the technology. The spokes are not intended to replace specialised cardiac hospitals. Their role is to provide the first diagnostic step and, where required, initiate treatment before referral. The hubs are empanelled medical colleges, private hospitals and charitable hospitals with cardiac catheterisation laboratories. Patients transferred from spoke facilities can receive procedures such as angiography and angioplasty free of cost under the Mahatma Jyotirao Phule Jan Arogya Yojana, according to the official statement cited in the report.
This creates a chain involving several parts of the health system: a local facility that recognises symptoms, a technology platform that transmits and interprets the ECG, a specialist who guides the initial response, an ambulance or referral pathway, and a hub hospital that can provide advanced intervention. A failure at any one point can weaken the pathway. The supplied material does not provide performance data on ambulance availability, referral completion, transfer times or the proportion of patients reaching a catheterisation laboratory.
The five-year agreement with Tricog Health Pvt Ltd is another part of the operating model. The technology company provides software-enabled ECG machines, consumables and cloud-based ECG analysis services under the programme. This means the state’s expansion depends on a combination of public facilities, contracted technology and empanelled hospitals rather than on a single category of provider.
For rural and district-level healthcare, the model represents an effort to use digital connectivity to overcome the uneven distribution of medical specialists. A Primary Health Centre may not have a cardiologist on site, but it can still generate an ECG that is reviewed remotely. The value of that arrangement depends on whether the test can be performed correctly, transmitted reliably and acted upon quickly. It also depends on whether the patient can be moved to the next level of care without administrative or logistical delay.
The geography of the programme matters. Maharashtra’s initial network covered 12 districts, and its 2024 expansion added 22 more while excluding Mumbai city and its suburban districts. The network therefore reflects a deliberate focus on facilities outside the state capital’s main urban health system. The reported expansion to 2,415 spoke facilities suggests a broad reach across government health infrastructure, but the supplied report does not list district-wise coverage or explain why Mumbai and its suburbs were excluded from the expansion.
The programme also illustrates the difference between access to a facility and access to a complete service. A patient may be able to obtain an ECG at a nearby centre, yet still need a transfer to receive definitive treatment. The hub-and-spoke structure is designed to bridge that gap, but its success cannot be judged only by the availability of machines or the number of facilities connected. It must also be assessed through the continuity of care from diagnosis to treatment.
The available figures establish a clear pattern: ECG activity has grown from 3,369 tests in 2020-21 to more than 2.33 million in 2025-26, while the reported network has expanded from 145 spoke facilities to 2,415. The project has moved from a limited district-level initiative to a large public health platform linking rural and district facilities with specialised hospitals. The figures do not, however, establish whether the growth has been even across districts or whether all connected facilities are operating at the same level.
The larger urban question is how states can make specialised healthcare accessible beyond major cities. Although the programme is focused on cardiac emergencies, its operating logic is relevant to the wider built and institutional geography of Maharashtra: people often live far from advanced services, while basic facilities are distributed more widely. Digital systems can help connect these layers, but only when physical referral infrastructure, public financing and clinical responsibility function together.
Maharashtra’s STEMI project therefore offers evidence of scale in emergency cardiac screening and referral. The health department data confirms a rapidly expanding network, millions of ECGs and tens of thousands of detected critical cases. The next level of evaluation will require information on treatment completion, transfer times, clinical outcomes, district-wise performance and the programme’s operation at the facilities added during its expansion. Those measures will determine whether the network is merely detecting more emergencies or consistently converting early diagnosis into timely care.
